01
SLEEVE + WEIGHT REGAIN
Sleeve → SADI-S
Principal pathway when inadequate weight loss or significant weight recurrence is the main problem.

Advanced options when previous weight loss surgery has not achieved the desired long-term result.
Weight recurrence after bariatric surgery does not mean you have failed. Obesity is a chronic biological disease. Hormones, metabolism, appetite regulation and the body’s defence of weight can change over time. The anatomy and effectiveness of a previous weight-loss operation can also change.
For some patients, revisional metabolic surgery can provide a powerful second step.
calendar_month Book a Consultation
The best revisional operation depends on what operation you previously had and why you need a revision.
Principal pathway when inadequate weight loss or significant weight recurrence is the main problem.
Often preferred when significant reflux, hiatus hernia, oesophagitis, Barrett’s or sleeve anatomy is the dominant issue.
Main definitive revision pathway after failed, complicated or poorly tolerated adjustable gastric banding.
Sleeve Gastrectomy is an effective operation, but some patients experience insufficient weight loss or significant weight recurrence over subsequent years.
This can occur because of a combination of biological and anatomical factors.
When further surgery is appropriate, the objective is not simply to make the stomach smaller again. The aim is to add a more powerful metabolic mechanism to the existing operation.
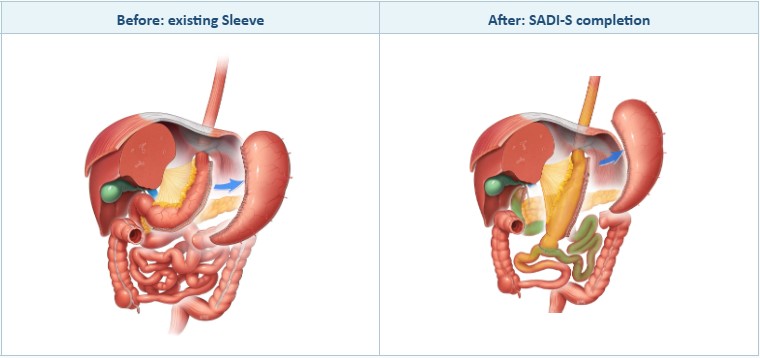
SADI-S – Single Anastomosis Duodeno-Ileal Bypass with Sleeve Gastrectomy – is one of the most powerful metabolic and weight-loss operations available.
For someone who has already undergone a Sleeve Gastrectomy, an important part of the SADI-S operation has already been performed.
The existing sleeve is retained.
The duodenum immediately beyond the stomach is divided and connected further downstream in the small intestine.
This adds a powerful intestinal and metabolic component to the existing sleeve.
SADI-S may be particularly attractive for patients with:
Unlike Roux-en-Y Gastric Bypass, the pylorus – the stomach’s natural emptying valve – is preserved.
SADI-S preserves the natural gastric outlet while adding a powerful intestinal and metabolic component.
These figures are evidence-informed callouts, not guarantees. Individual results depend on starting weight, duration of diabetes, pancreatic reserve, anatomy, adherence to follow-up and the definition of remission used.

Long-term studies report high rates of Type 2 diabetes remission after SADI-S, with figures around 80% in some long-term series. Results vary according to the population studied, duration of diabetes and definition of remission.
SADI-S also produces substantial improvement in:
Both operations are excellent metabolic procedures, but they have different strengths. For patients requiring substantial additional weight loss after Sleeve Gastrectomy, SADI-S can provide several advantages.
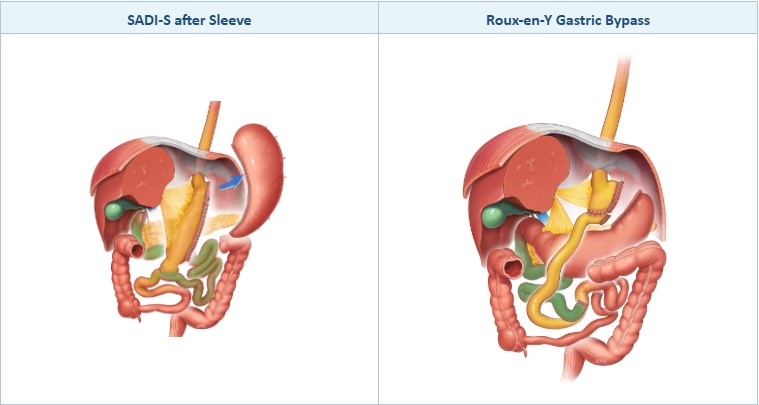
RYGB has a different anatomical configuration and is particularly important when reflux control is the primary objective.
For the appropriately selected patient, these features make SADI-S a particularly attractive revision when weight recurrence rather than severe reflux is the main problem.
Reflux following Sleeve Gastrectomy requires careful investigation. The important question is: why is the patient experiencing reflux?
Gastroscopy and imaging may be used to determine whether there is:
Where significant reflux is associated with a hiatus hernia, oesophagitis or an anatomical problem with the sleeve, conversion to Roux-en-Y Gastric Bypass – together with repair of the hiatus where appropriate – may provide the better revisional solution.
RYGB has an established anti-reflux effect and remains an important operation when reflux control is the primary objective.
The presence of reflux does not necessarily exclude SADI-S in every patient. In appropriately investigated and selected patients without a significant hiatus hernia or other major anatomical cause for reflux, SADI-S may still be considered where the primary objective is substantial additional weight loss.
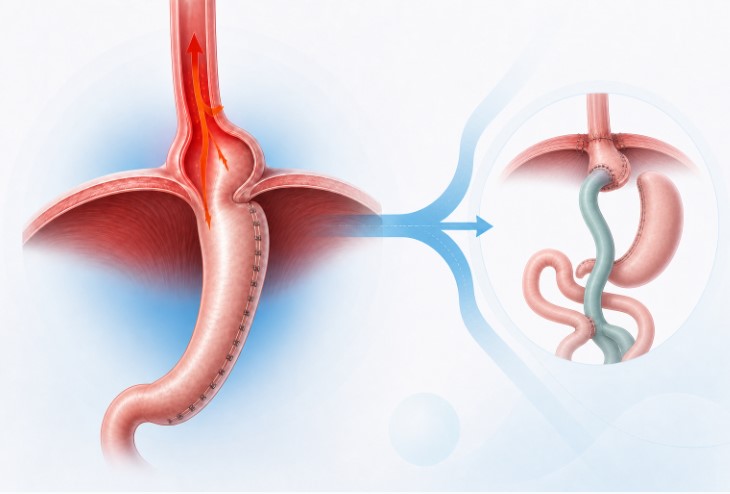
The decision therefore depends on the severity and cause of reflux, anatomy of the sleeve, presence of hiatus hernia and the patient’s weight-loss requirements. The operation should be matched to the problem – not simply to the name of the previous procedure.
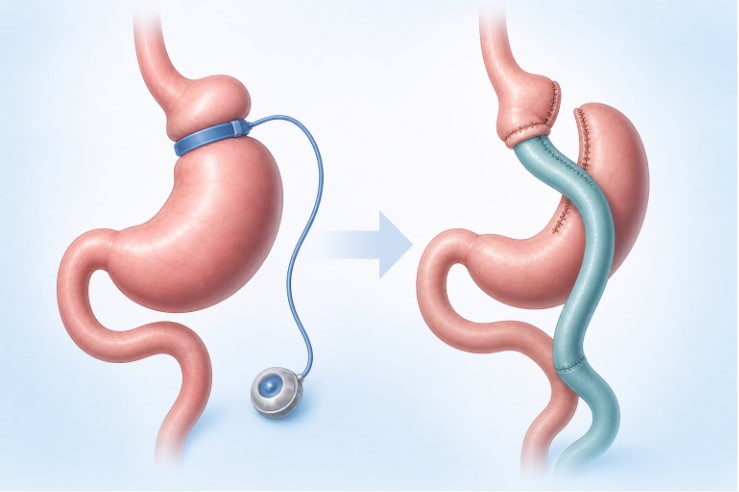
Adjustable Gastric Banding was previously one of the most commonly performed bariatric operations in Australia.
Some patients achieved excellent results. However, longer-term problems can include:
Gastric Bypass changes the mechanism of treatment from a primarily restrictive procedure to a powerful metabolic operation.
It can also provide a durable alternative to repeated gastric band interventions.
Safety Comes First
Some gastric bands can be removed and converted to Gastric Bypass during the same operation.
Other patients are safer with a staged approach.
Significant scarring, inflammation, erosion or other anatomical concerns may make a two-stage approach safer. The decision is made according to the findings in each individual patient.
The same intestinal bypass that makes SADI-S such a powerful metabolic operation also reduces the absorption of some nutrients.
Patients therefore require lifelong supplementation and regular blood testing.
Vitamin deficiency and protein malnutrition can occur if supplementation and follow-up are inadequate.
Lifelong nutritional monitoring should therefore be considered part of the SADI-S operation itself.

Revisional bariatric surgery is more complex than first-time bariatric surgery. Previous surgery changes normal anatomy and can create adhesions, scar tissue and anatomical distortion.
A specialist revisional assessment considers the complete clinical picture before recommending another procedure.
The objective is to understand why the previous operation is no longer delivering the desired result and then choose the most appropriate revision.
Weight recurrence after bariatric surgery is not simply a failure of willpower.
SADI-S is a powerful revision following Sleeve Gastrectomy when additional weight loss is the main objective.
SADI-S provides powerful metabolic effects and high rates of Type 2 diabetes improvement and remission.
SADI-S preserves the pylorus and avoids the gastrojejunal anastomosis and Roux-en-Y mesenteric defects.
Significant reflux, particularly with a hiatus hernia or abnormal sleeve anatomy, may favour conversion to Roux-en-Y Gastric Bypass.
Selected patients without significant hiatus hernia or other major anatomical reflux problems may still be candidates for SADI-S.
Roux-en-Y Gastric Bypass is an established definitive revision following failed or complicated Gastric Band surgery.
Lifelong nutritional supplementation, blood tests and specialist follow-up are essential following SADI-S.
SADI-S is one of the most powerful metabolic weight-loss procedures available. The amount of additional weight loss following revision depends on your starting weight, previous Sleeve Gastrectomy, metabolic health and other individual factors.
Yes. SADI-S has a powerful metabolic effect and studies have demonstrated high rates of Type 2 diabetes improvement and remission. Long-term SADI-S literature reports remission around 80% in some series, although individual results vary according to diabetes duration, medication use, pancreatic reserve and the definition of remission.
It depends on the reason for revision. When additional weight loss is the main objective, SADI-S may provide greater long-term weight loss in appropriately selected patients. When significant reflux is the main problem, particularly with hiatus hernia or abnormal sleeve anatomy, Roux-en-Y Gastric Bypass may be preferable.
Possibly. Reflux should first be investigated to determine its severity and cause. In the absence of significant hiatus hernia or other major anatomical problems, SADI-S may remain an option for selected patients where additional weight loss is the primary objective.
Because SADI-S preserves the pylorus, food continues to leave the stomach through its natural gastric outlet. Classic dumping syndrome is therefore much less characteristic of SADI-S than Gastric Bypass.
SADI-S does not create the gastrojejunal anastomosis that is the typical site of a marginal ulcer following Roux-en-Y Gastric Bypass. Ulceration and other gastrointestinal complications can nevertheless occur, so it is better to describe the risk as reduced or anatomically different rather than zero.
Yes. Lifelong vitamin and mineral supplementation and regular blood testing are essential after SADI-S.
For patients with a failed, complicated or poorly tolerated gastric band, removal of the band and conversion to Roux-en-Y Gastric Bypass is an established revisional pathway. The best timing and staging depend on the condition of the stomach and surrounding tissues.
Sometimes. Some patients can have the band removed and the bypass performed in the same operation. Others are safer with a two-stage approach if there is significant scarring, inflammation, erosion or other anatomical concern.
If you have experienced weight recurrence, inadequate weight loss, reflux or complications following previous bariatric surgery, specialist assessment can determine whether another procedure may help.
Mr George Kalogeropoulos provides specialist assessment and advanced revisional bariatric surgery, including Sleeve-to-SADI-S and revision to Roux-en-Y Gastric Bypass.
calendar_month Book a Consultation